Fuck You, You Knew

A survivors response to the Royal College of Psychiatrists (2026) Position Statement PS04/26 – ‘Addressing the impact of non-recent child sexual abuse on the mental health of adults’

In August 2026, the Royal College of Psychiatrists published a “landmark” position statement on the impact of non-recent child sexual abuse. It seemingly acknowledges that survivors have been disbelieved, retraumatised, misdiagnosed, and harmed by mental health services. It recognises the relationship between childhood sexual abuse and experiences extending beyond traditionally defined PTSD, including substance use, dissociation, and psychosis. It acknowledges Dissociative Identity Disorder (DID) as a real and historically contested diagnosis, and that this controversy has contributed to survivors being underdiagnosed and misdiagnosed. It appears to confront the harms of psychiatric diagnosis itself: the medicalisation of distress, shame, stigma, diagnostic overshadowing, and the fragmentation of people across multiple diagnoses. Splashed across the pages, prominently displayed survivor testimony describes generations of sexually abused women pathologised as personality disordered, calling the personality disorder (PD) construct systemically harmful, demanding its abandonment. And, extraordinarily, the President of the Royal College apologises for the “avoidable” harm survivors have experienced within mental health services.

These seem like pretty bloody significant admissions. There are things in this statement that survivors, activists, and critical professionals have fought for centuries to have psychiatry acknowledge. There is something enormous about seeing them written down in an official statement from psychiatry’s own professional body. Some of what is contained in these 94 pages would have been almost unimaginable as an institutional position not very long ago.

My first response when I read it was: They can get fucked.

Perhaps I was supposed to feel vindicated. Here, finally, was psychiatry acknowledging things survivors have spent our lives trying to make it acknowledge. Instead, I felt incensed. Because acknowledgement without responsibility is an insult. These things didn’t simply happen to us. People did them. Psychiatrists did them. And now, after all this time, I was being offered a half-arsed apology from a PDF. I don’t want a half-arsed apology from a PDF. I don’t want to be told that survivors have suffered “avoidable harm” because psychiatry was sometimes insufficiently aware, insufficiently trained, or accidentally got things wrong. I want a person to look at what was done to me and my peers and name it; I want them to acknowledge that we objected while it was happening; I want them to tell us that we were right, that they were wrong, and that it should never have happened. I want someone to own what psychiatry – and psychiatrists – did to us. Instead, within a paragraph of its “apology”, the College is already looking after the psychiatrists. “This will feel like an uncomfortable and unfair criticism”, we are warned, of professionals who “dedicate their lives to helping their patients”, particularly those who “do work hard to get this right.” Harm becomes “unintentional”, caused by “what is considered best or normal practice”, lack of training or awareness, or healthcare systems and structures.

But you see, I. Don’t. Care. whether you “intended” to hurt me. Intention is not accountability. “Did you mean to harm us?” is a fundamentally different question from “Did you harm us, did you know you were harming us, and what did you do when we told you?” If it was “avoidable”, why wasn’t it avoided?

Flicking through, page by page, it’s startlingly obvious how professional innocence and need for staff safety is repeatedly preserved. Even in a document supposedly about the psychiatric harm experienced by survivors of child sexual abuse, considerable space is made for professionals’ own self-care, and potential to be harmed vicariously by hearing about our trauma. Elsewhere, clinicians faced with inadequate trauma services are described as potentially experiencing “ethical dilemmas” and “moral injury” when they can’t help but harm us. Apparently even our mistreatment requires consideration of how distressing mistreating us might be for them.

Somehow, throughout the entire document, unless they are patting themselves on the back, or comforting each other about how hard it is to harm their patients, professionals are entirely removed. Services seemingly run themselves, while patients are assessed, diagnosed, treated, detained, restrained, abused, neglected, and harmed by some nebulous, undefined power beyond the control of the profession. Psychiatrists magically appear when there is compassion, hard work, or good intention to take credit for – but when there is harm, suddenly nobody is holding the pen. Nobody in this document wants to be the person who did anything wrong.

The same instinct appears when the College approaches sexual abuse perpetrated within the mental health system itself (I say “approaches” – it generously apportions one whole sentence out of 94 pages). It tells us that it is important to acknowledge that, “even if rare”, some survivors were sexually abused within children’s mental health services. “Even if rare” is doing an extraordinary amount of work there. The harm is minimised before it has even been acknowledged. At no point does it say who is abusing the children (staff? patients?), while children confined and abused on adultpsychiatric wards disappear from the sentence entirely – their highly documented and widely shared experiences of abuse don’t even exist. Most extraordinarily, or perhaps not, nowhere is there an apology from psychiatry for the fact that children were (and still are) sexually abused within psychiatric services. Psychiatry is apparently prepared to (sort of) apologise for the harm it caused survivors of CSA, while quietly acknowledging that some of that CSA was actually perpetrated within its own institutions, by its own staff, without apologising for that. Bit too uncomfortable is it? Once again, nobody did anything. Nobody abused the children who were abused; nobody failed to protect them; nobody allowed it to happen. It just happened “within children’s mental health services”.

This is what makes the College’s repeated appeals to “lack of awareness” so difficult to stomach. Psychiatry did not discover the relationship between childhood sexual abuse and mental distress in 2026.

It has always known.

In 1857, Dr Auguste Ambroise Tardieu documented the sexual abuse of children, including abuse within families. In the nineteenth-century Salpêtrière hospital, Charcot encountered sexually abused women among those diagnosed with “hysteria”. Freud’s patients told him about childhood rape and sexual assault, and in 1896 he publicly connected childhood sexual experiences with “hysteria” and “obsessional neurosis” before taking a dramatic u-turn – subsequently (and disgustingly) relocating the origin of CSA into fantasy. Across these histories, knowledge of sexual violence repeatedly collided with theories which located pathology inside the people subjected to it; and within it all, psychiatry had the power. This was not an abstract disagreement about how best to conceptualise distress. Survivors of sexual violence were disbelieved, detained, confined, sterilised, subjected to electroshock, insulin comas, lobotomies, and other damaging and even deadly interventions. Their resistance itself often became – and still becomes – evidence of pathology. Their accounts of what had happened to them were – and still are – transformed into evidence about what was wrong with them.

The College did not officially exist when this history began, but this is part of the intellectual and institutional ground on which it was built. The College’s predecessor, the Association of Medical Officers of Asylums and Hospitals for the Insane, was founded in 1841 – right at the heart of these early academic and clinical discussions. You do not get to inherit the authority, knowledge, and professional lineage of your predecessors while becoming historically weightless when somebody asks who bears responsibility for what that profession did, hiding behind words like “normal practice”. “Normal practice” is not the fucking weather. Professions create normal practice. They teach it, publish it, defend it, reproduce it, and enforce it. If generations of survivors tell you that your “normal practice” is harming them, you cannot indefinitely call the resulting harm an unfortunate consequence of insufficient awareness. If we told you that you were hurting us and you carried on, the problem was never that you didn’t know.

I am a survivor of child sexual abuse, and sexual violence as an adult. This has been the heart of most of my interactions with mental health services for the past 14 years. Like most people with my history and presentation, I was labelled with personality disorder. I was later diagnosed with DID and trauma-related psychosis, but the harm was already done, and continues to be done. This position statement isn’t abstract for me, it’s about my life. Not only that, but my name appears twice in the citations – my own survivor testimony used to create the document. Putting aside my anger, I tried to read it with some sense of objectivity, there were some good things – DID was being recognised; psychosis was too; personality disorder appeared highly criticised; and ‘false memory syndrome’ was finally put to bed. There were things I disagreed with also, such as the conclusion that formulation was the way forward, with absolutely no consideration for how many survivors experienced formulation as exposing and unsafe. Nobody appeared to have thought about the administrative usefulness of a diagnostic label in retaining a person’s confidentiality, dignity, or sense of control. I guess none of them have ever thought about what it would be like to submit a document detailing all the ways you were sexually abused to the local council to get a blue badge, or to your university to get reasonable adjustments…“What happened to you?” sounds wonderfully humane until the resulting formulation containing your most shameful and humiliating secrets is taken from you and forced to travel through bureaucratic systems, baring your soul to anyone and everyone who works at a desk. There was also an overall sense of the statement lacking teeth. DID was recognised, but there was no statement that the College would be pushing for NICE guidelines for dissociative disorders. Despite overwhelming evidence of the link between CSA and self-harm/suicidality, the words “self-harm” were only used twice, while suicide wasn’t discussed at all – there was no guidance on how this should be approached in practice. I wondered if they had perhaps published the first draft instead of the finished document. Where was the actual change it implied it was creating? It became a bit much, I had to have a break. As angry as I was upon the first reading, it was only when I came back and read the statement again after a few weeks that I realised it was actually even worse than my first impression.

On my first reading, my eyes had been drawn to the large, brightly coloured quotations scattered throughout the document. They say the things survivors have been screaming at the mental health system for decades: “Don’t attach the sticky label of borderline personality disorder”; “The personality disorder construct is systemically harming childhood sexual abuse survivors”; “We have known about this harm for many years”; “It is time to abandon the ideas behind this diagnosis”. One contributor says that while working in a personality disorder service they realised almost every patienthad been sexually abused as a child. Another says that if you disclose childhood sexual abuse and you are a woman, you are more than likely to end up diagnosed with personality disorder. It felt extraordinary reading these in an official College position statement – no wonder I thought the College had admitted something enormous.

Then I read the document again without reading the bright boxes, and nothing happened. Remove the survivor quotations from this supposedly co-produced document and the position statement remains intact. There are no holes in its argument, no missing steps, no paragraphs rendered incomprehensible because the knowledge on which they depended has disappeared. The survivors’ words sit visually front and centre, but the institutional argument does not depend upon them.

Look at what happens when those survivor voices collide with the College’s actual words.

Survivors say the personality disorder construct is overdiagnosed, systemically harming survivors, and should be abandoned. The College says “a proportion” of survivors have been treated in personality disorder services, which “have often been the only specialised psychological services to provide long-term care for patients with complex presentations”. Patients are described as “obtaining a diagnosis of EUPD” to access that treatment – as though we wandered into a hospital and picked one up at the gift shop. When the harms they don’t want to acknowledge around personality disorder are discussed, the institutional acceptance and authority disappears, and we are left with “survivors describe”, instead of “personality disorder is harming”. The college immediately reminds us that personality disorder “remains a controversial area within psychiatry”. Then the statement explicitly pivots to tell us: “This isn’t a matter of contested concepts, disputes about labelling or diagnostic models”, before criticising NICE for allowing PD to be diagnosed without structured assessment or collateral history – as if NICE guidelines themselves do the diagnosing. Later, the statement recommends (on the basis of survivor work which I contributed to) that specialist trauma services need to be separate from personality disorder services, while also, incredibly, concluding that despite this, “a significant number of survivors may not require specialist trauma services”. (Deep sigh). The personality disorder service survives. The construct survives. So does the contradiction of knowing that the people supposedly belonging there are overwhelmingly survivors. Specialist trauma services probably aren’t even that important.

The College has found an ingenious way to borrow the radicalism of survivor testimony without adopting its conclusions. Survivors are given visual prominence while the institution retains deniability. Their words make the document look brave, while in reality, nothing new is said. In the most incredible display of cowardice, the statement even tells us that these quotations are personal perspectives which “do not necessarily represent the views of the College”. That matters. Rape Crisis, responding to the statement, praised the way survivors’ “truths are rightly front and centre”. I initially read it similarly. But, in reality, their truths are front and centre on the page. They are not front and centre in the position.

This is not what co-production means. Co-production is not writing an institutionally comfortable document and decorating it with survivors’ words in pretty boxes. If survivor knowledge has no consequence for the argument, if it can be removed without changing its meaning, and if the clearest demands can be printed in enormous coloured letters while the actual position walks straight past them, then their presence is simply stolen legitimacy for conclusions they did not produce. And perhaps that is what I find most unbearable about this statement. Psychiatry cannot say that survivors have not told it. It cannot say that the critique was unavailable. It cannot even say it failed to hear the survivors involved in producing this document. You heard them closely enough to transcribe them; you heard them closely enough to type up their words; you heard them closely enough to put them in brightly coloured boxes. And then you carried on.

But this is bigger than some brightly coloured boxes. The boxes are simply a reflection of the problem that runs through this entire statement, and through the history it refuses to acknowledge. Psychiatry knew sexually abused women had been sexually abused, and diagnosed them with hysteria anyway. Psychiatry knew what had happened to survivors while it confined them, pathologised them, sterilised them, electrocuted them, lobotomised them, and subjected them to treatments that harmed and killed them. It knew when generations of survivors told psychiatrists that their disbelief, theirdiagnoses, their restraints, their detentions, and their withdrawal of care were harming us. It knows that children have, and continue to be, sexually abused inside the institutions psychiatry itself created and controls. It knows what happens to survivors funnelled into personality disorder services, because survivors have been telling it for decades. It knows because its own 94-page statement says so. And where survivors have gone further than the College is prepared to go, it knows that too, because it has printed their words in separate boxes, and added a quiet disclaimer.

This is not a problem of awareness. You knew what was happening to us. You knew what had happened to us. You knew what you were doing to us. We told you. Other survivors told you. Your own literature told you. And still, apparently, our suffering wasn’t sufficient to make you stop.

So fuck you. You knew, you still know, and nothing in this document can convince me that you have any intention of changing anything. I don’t believe that you are sorry. I don’t think you even know what the word means.

Wren Aves

It was clapping for the NHS that made me realise I had trauma

dark image with light making a silhouette of a face in profile. Photo by Engin Akyurt: https://www.pexels.com/photo/silhouette-photo-of-woman-1446948/

I think it was clapping for the NHS that made me realise I had trauma.

In hindsight of course I knew that what I’d been through was traumatic but I also minimised it, the memories were blurry, and the real stonker – it saved my life therefore I wasn’t allowed to wish it hadn’t happened, that would be wishing I was dead.

That’s the thing about mental health services and sections, they operate crudely, bluntly, they come in too late and too harshly but, by the skin of their teeth, they sometimes just about manage to do the job to the bare minimum standard and because of that remain just out of reach for the full force of a survivor’s anger. 

Or that’s how it is for me.

I care deeply about the provision of free-at-point-of-use healthcare, I would never want my critiques out of context to detract from that and I most certainly don’t see the rise in private day patient programmes as the solution.

Two of the leading of these private services are lead by the two psychiatrists I’m talking about.

I was in and out of hospital for a few years age 16-21 but it’s the final, adult admission that was so much worse than any other. The hospital had a reputation, I knew before I went in that it would be better to be literally anywhere else, but illness and geography meant I didn’t have a choice. 

As soon as I was admitted I begged to be transferred but patient choice was long ago thrown out the window for a sectioned psychiatric patient. It wasn’t until I read my notes years later that I really understood CCG’s and the funding backdrop.

Anosognosia is a key symptom of anorexia. You can see your weight going down, your intake going down, your behaviours damaging your relationships, life falling apart before your eyes and your mood plummeting, any rationality blurring and fragmenting and yet somehow believe that it’s not that big a deal, other people are making it a big deal, you will change, you can sort it out, if only you can find the right brand of yoghurt, if only it can be fixed by having an additional chocolate bar and slice of toast.

“I don’t need to be inpatient, just give me another change, I increased my meal plan by 100 kcal, I am better off at home” she says, weighing something ridiculous (I’m not going to say my weight, but if someone reading this is going to trigger themselves I’m sure they already know what a sectionable weight means). 

So yes I was a risk to myself, had no insight or understanding of the risks of starvation and wasn’t going to consent to medical monitoring or take the action required to stabilise my risk. In the face of that, psychiatry, as well as my mother, contend that “for your own good” you need to be in hospital.

To this day I have no idea how to feel about this? Would I have died? Would I have found my own way through? Who would I be today if what happened next hadn’t had to happen? What would it mean to me if what happened didn’t have to happen, I guess I tell myself it had to be this way because of how painful it is to imagine a world that’s not so cruel. 

Where hospitals places of care and restoration, nurturance and healing and not lunatic asylums by any other name, an extension of a carceral system, a place to lock away the undesirables, to delineate madness from sanity, to punish those who don’t conform and who scare the rest of them.

Anyway, I remember how scared I was when I realised the ward was locked. That I, specifically, was locked on the ward. That legally I was not allowed to leave. Legally I had no agency anymore. I was clinically determined unable to make decisions about my care, I was a risk to myself and couldn’t be trusted.

Other patients, voluntary admissions, could in theory leave, but in practice we were now all locked into this corridor of 20 beds, a meeting room, two dining rooms, two bathrooms, a kitchen and a central sofa and tv, seemingly sitting in the middle of the corridor but theoretically a communal space where we had to eat evening snack infront of a cooking show in the vortex of what happens when all the anorexias form a force field around which we orbited, getting closer and closer to that food-obsessed centrifuge.

The days were bleak. Usually waiting on tenderhooks to argue with a psychiatrist or dietician about how terrifying treatment was, how uninvolved in care planning we were, having to make desperate pleas and pitches to ward round to have leave requests or meal plans discussed and, when they did show up which they seemed to schedule with casual contempt for “I’ll see you tomorrow” agreements, hours or days later to be told you had less leave than you’d asked for, no meal plan change allowed, sorry we know best, sorry you can’t cope I guess you’ll just have to keep not coping whilst also not being allowed any freedom or social contact that might give you the means and strength to carry on, oh you’re jogging in your room now? Why would you do that? You must be causing trouble, not complying, do you want to be here forever? If you keep doing that you won’t get any leave at all.

You see, despite being sectioned on the basis of having no capacity to understand your own risk and behaviour, you are now going to be scolded, castigated, bullied, punished and have it held over you that you engage in behaviours that aren’t “helpful” or conducive to the goals we’ve set for you (“recovery”) or the goals you’ve set yourself (getting the fuck out of here asap).

Most of the trauma was in that contempt: 

Being held down to be nasogastrically fed and whilst a nurse sneered “what did you think would happen”. 

The transgression: I didn’t butter my toast and believed the feed would just constitute the calories of the butter, not the whole meal.

Being laughed at when I insisted not eating animals was a moral tenet and not a restrictive one – the implication, barely concealed, that an “anorexic” having ethics was risible. 

I was broken by the stripping away of any identity, any interests, anything I had found my self worth in being dismissed as “illness”, any assertiveness about who I was and what mattered was obviously “the illness talking” and “now is not really the time to care about that, you don’t have those choices”.

The euphemisms in my notes state “had to be constantly reminded to sit down, which she refused to do until further staff intervention” – my memory tells me this involves being pushed into a chair, held down, sat on.

The most visceral memory: kicking and screaming and being held down by 4 nurses whilst a 5th passed an NG tube. Pleading to be allowed to just drink the fucking supplement, that it should be offered to me for drinking and being restrained instead.

In a sickening, disorientating disappointment, when I got the stack of notes from the 9 months I spent in this hospital, this incident wasn’t mentioned. 

I was sure restraints would be documented by my guess is that a bit of  “manhandling” – pushing young emaciated women around – wasn’t classed as restraint.

Then there was the vicarious trauma of hearing everyone else’s cries, the woman who fought back and got taken to the general psychiatric ward “until you’ve calmed down”, the women who were in and out of that ward every few months, the woman who had been there for a few years, the woman who died on leave and being told that it wasn’t really our business to be furious with the psychiatrists for not protecting her, or maybe contributing to making her life unliveable.

I was given therapy whilst on the ward, 14 sessions documented in great detail in my notes by a therapist whose stance confounds me. She found me, “defiant… confrontational…challenging…hostile…resentful…attacking… aggressive…. defensive…aloof…contemptuous”. 

It didn’t seem to occur to her that the walls I put up protected me from the contempt of the staff, the disempowerment of the ward, the endless torture of having to face your greatest fear 6 times a day, deal with your mental illness and intrustive thoughts in every gap, be scolded for being ill in the place that is supposed to be knowledgeable about your illness, that you might, I don’t know, maybe be a bit cross about it all? 

When I expressed distress about being on the ward, anger towards staff or other patients she encouraged me to get to know them or to take part in groups. She couldn’t hold space for me to process what was happening to or around me. And when I picked this up and didn’t bring it up again, she noted our relationship was improving. 

The final therapy session before I discharged myself I cried “like a very small child” about being granted less leave than I had requested, I felt “insulted and humiliated”. I cried the tears of a trapped, lost, desperate, dehumanised, humiliated, lonely young adult, and she asked me if I was not crying as I cried as a child when my mother left me to go to work.

It made me laugh that that was the last interaction we had. As if she hadn’t heard of Ockhams razor. Or the cigar that was in fact a cigar. I was crying because the hospital was a hellhole and I knew I was not getting or going to get better. Because I knew I was leaving more “’damaged” than I entered.

My belief is that in a state of malnutrition, a physiological famine trauma, whatever the cause, our nervous systems and limbic brain is picking up information in a primitive way. We absorb relational trauma in a similar way to childhood trauma because we are regressed to our basic survival functions as we were then. When we are met with harshness we don’t need to have had a neglectful caregiver to begin to demonstrate signs of neglect and abuse. 

I have had to spend so long arguing that I don’t have causative trauma preceding my anorexia. I have trauma caused BY the anorexia, and more so its treatment that happened to save my life and caused the refeeding syndrome it was meant to protect me from, that managed to end the revolving door and be my final admission.

By making the experience so awful that I discharged myself from inpatients and then outpatients and then when I relapsed never sought help and put my family through so much having to cope with me on their own as we muddled through it until I galvanised myself to address this independently. 

Sometimes when I see eating disorder campaigns calling for better access to services it makes me so sad and angry, I don’t want more people to go through what I did. We need life saving interventions and anyone who needs their life saved, at whatever weight or stage these illnesses have made their lives unbearable.

But until services are not premised on a punitive ethos, to negatively condition anorexia sufferers out of the illness, I want to urge people to be careful what you wish for. Despite the layers of denial and the cognitive impairments to insight, we do know the illness no longer protects us from pain and instead causes it, we don’t need a hospitalisation driven by the desire to tell us “look where your silly little thin-fixation leads you, let this be a lesson not to lose too much weight”.

No amount of awareness raising seems to have changed the underlying assumption that madness = badness.

I feel like I should be caveating what I write with an endless stream of self-awareness. I know that I was distressed, anosognosic, rude, loud, difficult, non-compliant, disruptive, violent, symptomatic and in danger. I know that these interventions were in response to that and yet I still found them traumatising. I am not writing to present a solution – I don’t know what could or should have been done instead within the constraints on the system and the situation – my visioning for a future ideal would be a completely different system from the ground up.

The prevailing paradigm in mental health is punishment – giving the excuse as “institutionalisation”, the aim of eating disorder wards is to be so awful you keep yourself well enough to stay out. Despite many people requiring repeated admissions, the paradigm remains the same and staff admonish you get “get out and stay out”. 

This is somewhat effective, I had three admissions, my third being the most horrific and that experience did motivate me to “stay out” although it meant I was left unwell and without support, too afraid and hurt to engage with services but unable to take care of myself.

It’s not overwork or bad apples that make staff cruel – of course most staff are exhausted and underpaid and some get into the job because they like power over vulnerable people, but that focus distracts from the fact that institutions are set up to dehumanise mad people, a strange mix of infantilisation (you don’t know what’s good for you, I have the power) and chastisement (why are you doing that?). You are non-compliant, resistant, you need to be trained to not get attention for your bad behaviour.

Something has to overcome the cognitive dissonance of a person sectioned, and therefore deemed not to have decision making capacity due to illness, who is then castigated for behaviours (symptoms) and treated as attention seeking, troublesome, wilfully sick, who thinks she’s special, who should take responsibility

It seems that some of this comes from not understanding mental illness, even well meaning staff ask “why are you doing this to yourself”, “why don’t you want to comply and get out” as if they don’t understand the reason people are on the ward.

Alongside punishment, or a sub-category of it, is coercion and threat, most admissions are forced or coerced, wards are locked (I don’t know why I was surprised but realising the ward was locked was a horrible shock to me) and compliance is gained with threat of worse treatment. On an eating disorders ward the ultimate threat for distress was transfer to the general psychiatric ward which occasionally patients would disappear to for 24 hours to be sedated.

Units are protected by invisibility, although OTs, dieticians, social workers and psychotherapy came onto the ward, the team was permanent and complicit. No external professionals were coming in or asking questions. Psychotherapy was particularly complicit – criticisms of the ward were psychoanalysed away from their material reality – I was told I should “get to know” other patients, “find things in common” and “get involved in activities” when I told of bullying, abuse, screams of distress, competition and loneliness. An episode of extreme distress at not being granted leave or given reasons was related to “not getting what you want” and she asked “is this like when your mum left you to go to work”.

Dehumanising patients also involved mocking us – for me my veganism was mocked (although veganism presents a conundrum in eating disorder services, and should be examined and possibly challenged, laughing at someone telling you they care about animals as if it’s not possible to have both ethics and anorexia, as if every belief is a symptom is mocking and cruel) as well as compulsive exercise (yes watching someone jog on the spot and then try to avoid detection is humourously pathetic, I know it’s a bleakly funny sight, but laughing outright at a persons distressed compulsions is also cruel).

Diet culture is endemic in ED services and a lot of comments showing anti-fat bias get made – whether about gaining “too much too fast”, determining a maintenance plan at a conservative BMI, telling patients they “won’t get fat” and so on. 

I’m going round in circles here but to reiterate – dehumanising patients looked like, being mocked, being threatened (with transfer, section, tube feeding, restraint, losing leave), being endlessly reminded I was on a section and my consent was not required for tube feeding, being excluded from care planning and having unreliable, irregular meetings with the psychiatrist, being manhandled (although I remember being restrained, this remains completely undocumented in my notes. I can only conclude that it didn’t need to be written down as it wasn’t a formal restraint, just the pushing around and holding down an underweight young women who didn’t require much force to be overpowered), being shown a lack of compassion or any acknowledgement that my behaviours were a symptom and not a conscious choice or measure of my character.

A word to finish on nursing observations, 1:1 observations, on the toilet, in the shower – where your showers are timed for being too long, your bowel habits are commented on and, with new policy, nurses will wear body cams – is humiliating. It is predicated on humiliation because if you do exercise or purge whilst being observed you will either just be told “don’t do that” or restrained but mainly the threat is that if you do behaviours you won’t come off observations so the primary threat is the continuation of the humiliation and the admission and lack of leave, independence or autonomy. At no point is recovery or wellbeing mentioned.

It’s incredibly painful to speak about what happens on these locked wards. I was ill and vulnerable and left the hospital more ill and more vulnerable, at a higher weight but traumatised.

Because of this “access to services” is not what I want Beat to be asking for; services need to be transformed. I also don’t want “Accommodations for autistic patients” or any other small accommodations that make treatment less worse, not least because these won’t be applied because no one wants to make the experience less traumatising in case patients “like it” and “feel safe and cared for” and become “institutionalised”. I think this is more or less a straw man, most people want their liberty, most people who prefer hospital to independence is because of how bad life is outside not how great hospital is inside. Of course both repeated/long term admissions and proper supported living would make you a “drain on the state”, hence the system we have now. Until the idea that treatment must be horrible to prevent relapse, rather than effective is shaken then I cannot bring myself to ask for crumbs.

I believe many suicides attributed to the illness are a response to the “treatment”. Facing your worst fear 6 times a day every day under threat and coercion with little support or compassion, possibly brutally with restraint and tubes – not wanting to live whilst experiencing that every day? Yeah, I felt like that too.

It’s not much use saving someone’s life if they leave with so much trauma they don’t want to live it 

I can’t remember where I found this quote but it was written: “The treatment of AN, the violence, the behaviour modification, EDUs, who services decide to let die or forced to live”.

A section and enforced inpatient stay including force-feeding with a naso-gastric tube did in fact save my life. I am ambivalent about that. I am not uncomplicatedly grateful. I will criticise the clinicians, the institution and the system. I am still here.

I am actually now a therapist and that just makes me more critical, I can understand why decisions are made and things are said because I know the prevailing beliefs both psychoanalytically and psychiatrically and institutionally in the NHS. None of this makes it OK.

I don’t actually want to see a world where no one has anorexia, it’s an illness that is like 80% genetic in cause and has been around and documented for many hundreds of years and possibly has always been within human genetic diversity. Arguing for eliminating it would be eugenicist. I want us to be held, supported, fed and allowed to explore a meaningful life without being subjected to violence and correction.

I don’t want to see my experiences “formulated” – the diagnosis of anorexia nervosa is very accurate for me, it describes most of the compulsions, fears and delusions I experience accurately, when I experience them very intensely I say “I don’t feel well” because I see them as symptoms of a chronic illness, I do not agree that “madness is a sane response to an insane world” in my life – I have a brain that was predisposed to, and then developed, an incredibly strong fear or food. 

It’s kind of just bad luck, but it’s also who I am so I don’t see it firmly as good/bad although it certainly makes my life quite difficult, now I live with it and manage the trauma I endured in its “treatment”.

Mental Health Professionals Need To Help People With DWP Processes To Save Lives

By @444blackcat

I’m a AMHP an a MH social worker in an Adult Mental Health Social Care Team we used to be integrated with Health but the Care Act led to a split We have average caseloads of 40 people the vast majority entitled to state benefits ESA and/or PIP an repeatedly they have to prove that entitlement again and again. All workers need to consider the impact this has on people, not only the financial impact but the stress of having to share their personal lives with the DWP It’s an essential part of our job including if you’re a CPN OT or Lead Professional to make sure you help with forms or get someone who will, write supporting letters an make sure people know they can put your contact details on.

Please don’t think of this as a favour, more as an essential part of your role and yes nag the Consultant or GP to do their bit. I’ve never had a DWP worker complain there’s too much evidence. And to appeal perhaps to the selfish side of things. A person been denied benefits can easily lead to a crisis giving you more work an your organisation more costs We’re lucky enough to have a great CAB worker but they are overwhelmed but resources are online to make sure people get the points they need and deserve.

5 Ways To Help

By Tony Roberts. Former RMN and Public Health Specialist @FosterChangeUK

I used to work as a MH nurse for a CMHT. Occasionally, some patients were re-referred or dropped into crisis for an unknown reason. I had a colleague who always dismissively suggested that it was “just because their benefits are up for review”. Their cynical hypothesis was that the patient was manufacturing a “crisis” for the purpose of getting their benefits renewed. Once this objective was achieved, the patient “wouldn’t be seen again for two years” Our response, therefore, should be to ignore said “crisis” (air quotes were a common thing for this colleague). We should refuse to assist or write a letter, because that would be rewarding and perpetuating their manipulative behaviour.

I don’t think this is an uncommon view in MH services. It is a failure to see how much our mental health (and I do mean for all of us) hinges precariously on our financial stability. Some of us fortunately have a wider tolerance for financial upset – we may have savings, a generous credit limit or others we can lean on for help. But for many patients of mental health services – especially those dependent on welfare – this tolerance is a knife edge. Any slight change to their finances can have a catastrophic impact on their ability to live a humane and decent life. And it’s not hard to see why, if we choose to spend a few minutes thinking less cynically than my former colleague. Paying rent and bills is a pretty non negotiable chunk of income. From what is left, we have to prioritise. Hopefully, there is enough left to eat healthily, be able to get into town, heat the house when it’s cold, visit friends and relatives, watch some TV, have phone credit, get to appointments, and do things that make our lives more enjoyable – maybe odd treat, rewarding activities or a Netflix subscription.

But what if that financial stability is threatened by the Brown Envelope of Doom? What do we cut back? Do we downgrade our food? Cancel Netflix? Walk into town in the rain? Stop seeing the people we love? All the things that keep us well are under threat. And some people don’t even have those luxuries to cut back on. Reduced income threatens the essentials – bills, rent – risking eviction, arrears, homelessness. The stress of a benefit review cannot be underestimated. They threaten everything a patient has. Their entire life.

But what can we, as MH professionals do about it? Easy. Here are 5 things:

1 – Spend a few minutes of your time familiarising yourself with the DWP and review process.

2 -Talk to patients about their very real concerns. Find ways to mitigate the potential impact, help to take some of the distress from the process by planning contingencies.

3 – Talk to colleagues who know more than you – social workers, welfare rights etc who can give you and the patient advice.

4 – Offer to assist the patient through the process. It is hard enough to navigate as it is, without all the additional stress it causes. Give patients some spoons and take some of the load off them.

5 – Unlike my former colleague, write that letter of support. DWP letters often ask specifically about things like diagnosis, treatment, medical opinion etc. You may have views about the “validity” of such “constructs” That’s fine. But now is NOT the time for your philosophical views on psychiatry. Now is the time to sign a letter that means your patient won’t starve, be isolated, cold or desperate. Save your philosophy for Twitter. Sign the letter.

Time To Talk About Positive Mental Health Charities

How a happy philosophy may be out of step with survivor experiences

Image of Kandyman robot who enforces happiness for the Happiness Patrol in Doctor Who

I write as a supporter of the voluntary and charitable sector in Mental Health. Many survivors prefer voluntary sector services to formal services. Voluntary sector services are often more culturally attuned and user led. Their services are more understanding of different personal identities and equalities. They do not have powers to section, medicate or control. The voluntary sector is there when statutory services discharge long-term service users due to overwhelming demand from new referrals. There are numerous examples of truly user led and compassionate services including Self-Injury Support, Leeds User Led Crisis Service, Speak Up CIC and local Hearing Voices Groups. NSUN lead the way in capacity building and championing user voices. 

There is direct action on social media led by coalitions of survivors, for example, the Stop SIM campaign, Recovery in the Bin (RITB) and Revolution LXP. Social action involves risk and courage for involved activists, many of whom will avoid public recognition because of danger to their jobs or benefits status if retaliatory actions are taken by authorities. I am not an activist and cannot do justice to grass roots and voluntary sector groups. This article is not meant to criticise the hard and underpaid work in this diverse sector but to provoke thought about how services need to listen to the needs of their recipients. 

I want to focus on the apparent happiness mandate from many local mental health charities. It is likely the positive directive is linked to outcome measures and the hoops jumped through for statutory funding. The now complete shift to outcomes reporting is in line with the Recovery agenda. In most cases, survivors have not developed the measures to evidence their expected successful journeys. It is difficult for voluntary sector groups to seek funding for core services when money may only be available for new projects. Ongoing users may be a hindrance to outcomes linked funding, which prefers those who can move on after six months preferably to independence and employment. Demand for services is hitting charities, as it does relentlessly for statutory services, but practice in the voluntary sector starts to mirror the time-limited Recovery framework which RITB has campaigned against. 

Before lockdown I visited a ‘crisis café’ occasionally. The ‘café’ would not admit people unless they were willing to fill in a paper questionnaire about how they were feeling and what led to their visit. At the end of the visit another questionnaire on the back of the form meant self-assessing how you felt after, and what services you avoided using that day due to the ‘café.’ I used to wonder how anyone in crisis could be expected to fill in two questionnaires. A one to one chat, limited to 15 minutes, was their sole service offer for three hours twice a week. 

I fill in questionnaires over the phone every month when I speak to an employment adviser from a voluntary sector organisation. Regular reviews involve questions like whether I feel loved, have energy, feel useful and am showing an interest in other people. The questionnaire is a no argument condition of receiving support. I do not care at all if the score has gone up or down. It is difficult to give ‘real’ answers in case you lose the service if it is viewed not to work. You have a relationship with the worker who asks the questions which means you answer in a generous way. 

Charities in the mental health voluntary sector adapted during the pandemic with online and phone support. A Zoom call cannot truly replace the chance to meet peers socially or share a meal. Many service users cannot afford the internet. The continued gap between meeting up and virtual help appears to have put more emphasis on social media messaging. Charities direct their time into social media pages which reflect positivity and wellbeing promotions. 

My local charity’s facebook page publishes poetry most of which does not relate to mental health experience. There is a new Feel Good Friday poster on there every week. Positive cod psychology sentiments such as “happiness is not by chance but by choice” and “you do not find the happy life, YOU MAKE IT” are posted for likes. During lockdown another local charity encouraged sharing photos from ‘wellbeing walks’ despite the fact that exercise was limited by law. 

Most social media posts from charities are about ‘reaching out’, asking for help or looking out for positives. It makes sense to try to keep spirits up but may feel invalidating to those who are bereaved or on low incomes. Happiness is at odds with the times we have been living through and it can feel infantilising and that we should be unaware of a world beyond our own ability to be mindful. 

The messaging can feel false, as survivors we know that there is no help even if you do ask it unless you can pay for private therapy. This applies mostly where you have a long history of mental health problems and are ‘known to services’ which say they have done all they can. To repeat this ‘ask for help’ message is insensitive when organisations should learn from our rejections. 

Where the voluntary sector promotes ‘wellbeing’ to the exclusion of recognising distress, there will be former members, perhaps those most in need, who disengage. Even before the pandemic, charities had moved away from social drop-ins. All groups must be labelled peer support though the needs of individuals in the group will be varied and negative discussion frowned upon. At the now virtual crisis café, it would not have been possible to mention my self-harm to other visitors, despite this being the reason I was there. Entry to voluntary sector support involves signing up to activity such as pottery classes, creative writing, art or cookery. It can feel like an Occupational Health department when these existed on psych wards decades ago. 

Overall, no-one asked service users nationally if they either wanted to move to the activity model or go it alone. Choice was taken away from us. It can already feel as though you are ‘other’ in a society where people have partners, homes owned outright, children, education and jobs you missed out on from being distressed. Charities could exacerbate this sense of ‘other’ and social exclusion unless they respond to their members who continue to experience severe distress. In an unattainable happy community, there is no space for those who feel despair. This atmosphere drives distress underground, so it is more likely someone could turn to darker parts of the internet such as ‘suicide forums’. 

Mental health experiences may not resolve and medication can lead to side effects which are a secondary impairment in themselves. We need safe spaces to talk about how these real issues affect us. Most of us know about the five ways to wellbeing or local walks so can try these in our own time if we find them of any benefit. When voluntary sector services are open, we need to be heard. I think of palliative care available to those with life-limiting conditions and the philosophy that helps patients to make the most of what life is left. Adopting palliative care approaches to those with ‘chronic’ and long-term suffering makes sense far more than flippant “don’t worry be happy” social media posts. 

As survivors we need to talk to voluntary sector organisation managers and start discussions about how we reclaim the debate. We understand that funding is hard to secure and want this to change. There may be ways to still do the paperwork but have spaces which respond to what we really need. A group could still be called ‘women’s group’ but discuss living with traumatic stress. A ‘happiness group’ could be a cover for discussing what to do when we feel like we can never be content. We need to talk about iatrogenic damage. I have a diagnosis of Borderline Personality Disorder but have had to explain to charity workers what it means and why I reject it. There is a training need with many workers with posts low paid, unless they have their own experiences or learn from members. The voluntary sector should facilitate and not shy away from discussion which may not fit with a diagnostic manual. 

It is already recognised that talking about suicide does not encourage someone to take their own life. If we start talking about realism then it is a relief and we do not have to be something we are not. It will not mean that we suddenly become negative and nihilistic. Individuals with mental health issues face huge challenges with poverty, loss, poor housing and unemployment. We cannot live in a Disney cartoon or pretend social injustice does not affect our peers. 

The voluntary sector workers can help in practical ways, for example going with members to face to face benefit reviews or writing letters. They can get onto the mental health team which has rejected a referral again. They can listen without judgement and not set the agenda topic. Until we lower the volume of the happiness rhetoric our personal stories and needs are not being heard clearly.  

Book Re-release- Mass Murderers in White Coats by Lenny Lapon


This books covers a range of psychiatric abuses but is of particular interest for current service users in helping us know the history of how Nazis treated psychiatric patients and our survivor history of resistance and organising against psychiatric abuses.

Lapon was a militant activist beginning in 1978 with Mental Patients Liberation Front in Boston (MPLF) and the Alliance for the Liberation of Mental Patients in Philadelphia (ALMP), participating in organizing, demonstrations, civil disobedience, advocacy and writing. He was arrested on several occasions and completed a 60-day fast against psychiatric oppression.

Review by Sharon Jean Cretsinger, Tijuana, July tenth, twenty-twenty-one

I am happy to see that Mass Murderers in White Coats (1986) by Lenny Lapon is now in a digital edition.  It is an impressive collection of essay and research that needs a much wider audience, especially now.  While this book technically falls in the category of non-fiction, it is structured more like a doctoral thesis.  This is not to say it is not eminently readable.  The style is spare and intelligently rendered.  I mention the overall construction of the book because the forwards and the appendices are important to the subject and should be read equally with the text.  Lapon’s updated preface (May 2021) serves to contextualize its significance in historical place-time.  He notes that the book is a kind of point-in-time look at the psychiatric inmates’ liberation movement.  It was an important point in time because it was at almost exactly then that the radical and resistant arms of this movement were effectively (and perhaps intractably) broken by the government.

In the original preface, the book’s objectives are carefully laid out:  to document the mass murder of “mental patients” by psychiatry in Nazi Germany and in the U.S (psychiatric genocide); to show common ideological roots of the killings in Nazi Germany and harmful, sometimes fatal, psychiatric “treatments” in the U.S.; to give the ex-inmate’s perspective on the oppressiveness of psychiatry, its violence and danger; to present excerpts from conversations with members of the American Psychiatric Association (APA) who are connected to Nazi Germany; to present a history of the organized resistance to psychiatry by its victims; and, to bring all of these issues into the light of public awareness.

The book achieves all stated objectives except for the last one.  Hopefully, wider access to this digital text will help to publicly illuminate the pervasiveness of contemporary psychiatric atrocities and the almost-lost history of radical resistance to same.

Relevance to Intersectionality and Identity

In contemporary culture, there are emerging and increasing texts and discussions about marginalization and identity.  Mass Murderers is important to this discussion because it clearly illuminates issues belonging to survivors of psychiatric atrocities.  It reaches back to Nazi Germany and documents real conversations the author had with Nazi clinicians.  This aspect of the book’s research is irreplaceable.  Appendix 3, “The Myth and Politics of ‘Mental Retardation’” bears a special mention.  This community remains one of the most oppressed in first-world cultures, with many individuals who carry this label still institutionalized and exploited for pennies a day in sheltered workshops.  The fields of psychiatry and related behavioral health disciplines support the dynamic through large-scale drugging with psychiatric pharmaceuticals and various abusive and reductive behavioral “therapies”.  

The author’s introduction makes the wealth of information presented in the text personal, and perhaps more importantly, relatable to “ordinary” folks.  Psychiatric and behavioral health abuses and atrocities can literally happen to anyone.  Yet, in the context of intersectionality, they happen more frequently to individuals who are otherwise marginalized such as people of color and those with disabilities.  As these narratives become increasingly visible, the perspectives of ex-inmates and survivors are crucial to this body of work, but often missing.  Mass Murderers is so valuable because it subverts basically every authoritarian attempt to control the narrative of the atrocities discussed.  The importance of proletariat scholarship in the narratives of the marginalized and the working-class cannot be over-emphasized.  This book is a beautiful example.

Relevance to the Present-Day, Ex-Mental Patients’ Movement

Particularly relevant in the context of today’s “movement” is Appendix 2, titled “Alternative Therapies Criticized and the Role of ‘Mental Health’ Workers in the Fight Against Psychiatry”.  When seen together with Appendix 5, “Psychiatric Inmates’ Liberation/Anti-psychiatry Groups*”, we find a comprehensive picture of a movement that barely exists today.   In place of most of the liberation groups listed in Appendix 5, we have many government-funded and pseudo-clinical organizations.  These “practitioners” and “non-profits” have replaced radical organizing groups with various “alternatives” ranging from the clearly self-pathologizing to complicated systems of contrived, facilitated communications such as the “Hearing Voices Network”, “Wellness Recovery and Action Plan (WRAP)”, and “Intentional Peer Support”.  The rhetoric of revolution and abolition detailed in Appendix 2 has been co-opted and replaced with these various pseudo-clinical “interventions” and “positions” such as “peer supporter” and “case management aide”.   Lapon states it quite simply in this appendix: “They make money off our pain and suffering.  Some of them have ‘anti-psychiatry’ conferences and invite a token ex-inmate or two.  As with other oppressed groups we buy into our oppression in various ways.”  

Mass Murderers in White Coats is ostensibly a book for those interested in doing serious antipsychiatry organizing.  These individuals may wish to go directly to the chapter five, “The Resistance:  A History of the Psychiatric Inmates Liberation Movement” to find inspiration.  There is also plenty for those who are interested in antipsychiatry and historic and contemporary psychiatric and behavioral health atrocities and their intersections with other forms of marginalization and discrimination.  Hopefully, this e-book will offer resources to readers and researchers interested in antipsychiatry, its intersections, and adjacent aspects of historical and Holocaust scholarship.  

I am now unable to talk freely about my mental health as I fear arrest

This account of my experience is purposely anonymised because I am not ready for those in my life to know the pain that mental health services and police have put me through. This began during a difficult period of my life in which I was the victim of physical, sexual, emotional and financial abuse in a relationship that I truly believed was impossible to leave safely. I had been under mental health services for most of my life not by choice and had made a lot of progress. Without being too graphic, the abuse started almost instantaneously and I was kept in line with the threat of harm to himself and me. He controlled me and he ran my life for nearly six months during which I attempted suicide a number of times. The police had a lot of involvement in my life at this point, every time I survived, I became more determined that I was the plague on this earth and that ending my existence would solve all the problems we see throughout society. I had graphic nightmares in which I survived and had to watch those around me be tortured and murdered and struggled immensely with trauma symptoms. 

My suicide attempts have been labelled as ‘a cry for help’ when in reality, every time I was saved, I thought I could feel someone else die as a result of my ‘failure’. At the time I wasn’t told about this but my local team and police force made a ‘crisis plan’ detailing how to ‘deal’ with me in a crisis and avoid ‘reinforcing’ what they believe to be attention seeking behaviours. This plan was in place for four months before I was made aware it existed and I was not shown a copy of this plan I had supposedly agreed to until two months after this. Six months in total.

The plan states that if I am found in public in a crisis situation, I am to be taken to hospital for a capacity assessment. If I am deemed to have capacity the officers involved must arrest me for any offence that they feel appropriate. 

When I was told about this plan the explicit instructions I was given were “to not commit suicide in a public environment”. I was also told that I could “do what I wanted in my personal space” AKA I can take my own life as long as it does not inconvenience any other people.

This plan has destroyed my faith in mental health and police services and has meant I am now unable to talk freely about my mental health as I fear arrest if I am honest with how I feel. I also know that I can’t risk surviving future crises and I am sure that if I was to get into such a desperate situation again, I would not walk it off. 

Mental health services are designed to treat a very specific range of presentations. As soon as you fall either side of their ‘worthy of treatment’ parameters you become a disposable commodity like I and so many others have. Knowing that those who should care have no desire to work with you is the total opposite of help. I was in a vulnerable situation and those meant to help me turned their backs leaving me in dangerous and damaging situations because of how they perceive my suffering. 

I am not a criminal. 

I am a survivor and I will not stay quiet any longer.

The Crime of wanting to die, my story from Scotland

For the past two years I had hid my shame and embarrassment. I felt like I was to blame, even though I was the victim. I was told I was to criticize, and it was my choice; my choice to be arrested and my choice to die.

My crime? I tried to kill myself, believe it or not, dying is hard, so I was slow, and I was able to be saved for better or for worst.

In 2018-19 I found myself miserable and just wanted to die, I was expiring the consequences of another person actions against me, I was expensing the symptoms of PTSD or C-PTSD. I did not see a way forward, life felt so painful, and I felt that my death was the only way forward.

I had just been discharged from my first hospital stays in a psychiatric unit. I was just kicked to the curb I had not been told what would be happening, I was told to go home in to the community with no preparation or help. Just after an admission is a time that the NHS have admitted increases rise of death though suicide. I felt so loss and hopeless, I stupidly publicity tried to kill myself, I regret it now, the police took me to the ED, and I was told “I had capacity” after the nurse talked to the police who voiced their concerns and the mental health team told them I was not feeling real depression and the trauma in my life was fictitious. How does one have capacity when I had actively tried so hard to be dead.

The police were left without much of a choice and arrested me. What choice did the police have when I was dead set on killing myself.

Believe it or not, being arrested when you did nothing wrong was traumatizing. Every day I carry the burden of my arrests and I feel my skin crawl with every mild flash back. I went through the normal booking routine, and I was informed that they did it to try and force the hand of mental health services into helping me and that I would most likely be out the next day. I complied with the whole booking proceed, and I was dumped in a concrete cold cell in a paper dress. My mug shot was taken and fingerprints. The police admitted I was mentally unwell and added several comments about how poor the local mental health hospital is, lack of bed and constantly having missing patients (over 200 patients reported missing in just 2 years). I was let go after 14 hours with not even a mark against my name.

This arrest just catapulted my problem and I spun out of control. I felt like I was marked with another label, the label of a criminal. I keep repeating in my head that I should have competed the suicide. That marked my second attempt to end my life and acted as catalyst for my year of hell.

Imagen being abandoned by the NHS at the start of your mental health journey, forced to live though the forced unparalleled consequences of actions that everyone saw as mental illness. A custody cell and under trained police officers is not equal to mental health support. Custody cells should not be used as an extension of the mental heathy system, they are not a resort to be use in times of mental health crisis. Police can not deal with people like me, I, by their own admission had committed no crime. The crime that they did arrest me with was a ‘breach of the peace’, an arrestable offence in Scotland

I find myself here today. Nothing has really changed; police are still being used as an extension of the mental health services without any of the training that come with it. Why should a health emergency be treated the same why as a criminal matter? Why is this acceptable?

How is locking someone up in a custody cell a punishment for trying to end one’s life? Why does someone need to be ‘punished’ for a mental health emergency.

If the NHS trust continues to view the police as a first responder for a mental health crisis, they should be open and honest about their use with the NHS mental health system.

Why did the NHS allow an 18-year girl to be locked up because of a lack of mental health services?

Mentally unwell or criminal? My experience of being criminalised for my mental health.

In June 2017 my life fell apart. I was raped and endured a year long police investigation into the matter. I had always had a good life up to this point but suddenly it was flipped upside down; I was out of work and struggling with thoughts of suicide and self-harm. My way of coping was to overdose and I was constantly in and out of general and psychiatric hospitals.

As some of the overdoses were away from home and, on occasion, I would abscond from hospital when in severe distress, the police decided to issue me with a Community Protection Notice Warning (CPNW). It read:

 “This letter should be considered as formal notification of your need to put these problems right to avoid further consequence. Please ensure you take the following action/s within the timescales detailed.”

The actions were as follows:

  • not to have any unprescribed medications on me
  • not to act or ‘behave’ in a way as to cause another person to believe I’m in danger of harming myself.
  • not to contact anyone by any means to make threats or allude to any thoughts of self harm or suicide. This includes my close friends and family.

In a time where “just talk” and “reach out for help if suicidal” narratives are everywhere, being under a police-ordered notice NOT to talk is incredibly isolating. It goes against all the research that talking about suicidal thoughts is crucial in managing them. It gives the police powers over my health, where they have no place. It is a violation of human rights.

Unsurprisingly, the letter didn’t help my feelings of hopelessness and my struggles to engage with mental health services. Instead of being instantly cured from my mental health problems and suddenly stopping the self-destructive ‘behaviours’ like the police had hoped, I continued to be admitted.  My admissions became a lot more severe each time, and I usually ended up in intensive care units. Health professionals would mention the CPNW whenever I asked about signing forms to leave, and they would constantly threaten to contact the police and tell them I’d breached the notice. Health professionals became an extension of the police force and I found it impossible to trust them.

Eventually in May of 2019 the police decided to issue me with the full Community Protection Notice (CPN). This is valid for 2 years and includes all the same actions contained in the  warning letter that I must abide by. Once when I was struggling I text a friend to say I was thinking of harming myself. She ended up calling for help and the police showed up, who told me I had broken my notice.

I have never felt more isolated than I am now knowing that if I do need help I can’t so much as tell a friend or even a family member. I’m not even allowed to tell my mum I’m struggling. What sort of life is that? If my family call for help, it’s me who will get arrested. The only people I’m allowed to talk to about suicidal distress are specified mental health professionals, yet they are the ones who’ve put me in this situation. My trust in them is at an all time low. Talking about my distress and asking for help is now a criminal offence.

Increasingly more people, often those given a BPD diagnosis label, are being arrested and sent to prison because of suicide attempts or their communication of extreme distress, despite the fact suicide has been decriminalised since 1961. More and more of us are ending up in the criminal justice system because of our mental illness. It seems we are seeing a resurgence of the criminalisation of the mentally ill by the back door, in the name of ‘public protection’.

If you genuinely want to help people like me, please start by just listening. Provide me with appropriate support, talk to me, offer me therapy – just don’t call the police.

The Double Life Of The Recovered Professional

In or Out

I find myself in a dilemma.

I have spent the past 15 years engaging in ‘recovery’. I have spent the last six years (or thereabouts) shouting about how utterly grateful I am to the services that ‘saved’ me. I have worked hard to come off benefits and pay my way. From being the most difficult patient, I have become the poster girl for the recovered individual. I have been an (unpaid) service user facilitator in a DBT group, I have a chapter in a book edited by a renowned clinical psychologist and I have delivered motivational talks to groups of professionals. The dilemma I find myself in is that I no longer believe what I have said. My dilemma is further exacerbated by the fact I work in mental health services.

I would not be writing this if my internal self was congruent with my apparent external state. I keep thinking, ‘well, I am in a much better position than I was 10, 7, 4 years ago’, and this is true to a point. I am not attending A&E every weekend; I am not getting myself so drunk, I wake up two days later; my financial situation is much more stable. I have been able to maintain a relationship to the point of marriage, and I am able to interact with others in a socially acceptable way. In all of that, however, I do not state I actually feel better.

I imagine I must feel better because I am not doing the things I used to do…although I am. Recently, my spouse went away for a few weeks and I was left to my own devices. I took a ton of codeine (not to harm myself, just to get off my head, to feel better), I drank a fair bit (a litre of whiskey in one sitting), and I self-harmed (pretty fucking badly in all fairness). Not having work to go to and actually still being as isolated as I was 10 years made brought home the stark reality of my existence. All I have done is supress how I feel, ignore my experiences and distract from reality. With work removed, I am scrabbling around, afraid of myself and wondering what the fuck is it all about?

I thought I wanted to be a clinical psychologist, but it turns many of them are narcissistic, egotistical, elitist sociopaths. Furthermore, the selection process for the clinical psychology training is based on many things, a key one having the ability to interpret statistical data. I’ve met too many clinical psychologists who are excellent with graphs yet not so skilled with people. As long as I adhere to their way of thinking, then I am doing just dandy. Any deviation from their thought processes, then we are being difficult, wilful, and defensive. Their toxicity is disguised, however, as they talk about trauma as opposed to personality disorders (which isn’t a bad thing, as at least experiences are being somewhat acknowledged). What further happens is that the good ones think, ‘fuck this shit’, and they leave. Whilst I’m definitely not a clinical psychologist, I’m at that point of wanting to leave. Everything I thought I wanted has fell around me, and I realise that recovery is but a concept coined by the professionals who have no peripheral vision.

As someone who grew up in the care system, what am I trying to recover? I was sexually, physically, and emotionally abused. I did not see my biological mother for over 20 years. My child was removed from my care. I have struggled, but been made to feel guilt and shame for my responses. I was instructed to hide old self-harm scars during DBT. We were not allowed to talk about self-harm within group, because of the risk of glorifying or romanticising it. I have been indoctrinated just as much as the people from my childhood indoctrinated me.

I work as a mental health care support worker. Some of the people I work with are genuinely nice people, but I see their limitations created by the system. Terms such as, ‘it’s personality’, ‘they’re med seeking’, and ‘they’re a nightmare’ are bandied around without thought or reflection. How offensive is it to term someone’s personality as disordered following a whole heap of childhood trauma? Why are we ok to dispense diazepam when ‘patients’ are not asking for it, but when they request it for the same problem, we no longer see it as a beneficial? What makes someone a nightmare?

What I am left with is a fear of someone finding out about me and my ‘stuff’. I work in an office with a whole bunch of mental health ‘professionals’, yet I am terrified they will find out my secret. This fear comes from the stigma I have witnessed and been subject to throughout both my non-working and working life. I was stigmatised as a service user with a diagnoses of BPD, and I am unwittingly stigmatised within my profession. There are mental health nurses who quite happily state that people with mental health difficulties CAN NOT work in mental health. When asked what recovered, ex-service users can do, they cannot answer, just that we shouldn’t be working in mental health.

Why can’t I find someone to talk to, without them trying to fix me? Why can’t I say, ‘you know, I feel shit, and there’s a good chance I will always feel shit given my start in life, but I accept that. I might self-harm from time to time, as safely as possible, I might engage in some other behaviours, but I am not asking anyone to patch me up. I’ll do that myself. I just want space to talk about it’? Why is this not acceptable? Why am I not accepted as I am, cuts and all? Why do professionals only care if you are ‘engaging’? Engaging in what? I have done everything asked and expected of me, and more. I’m lonelier than ever because I have been trained to put up and shut up.

The mental health sector does not believe in the recovery they try and push, but they do not recognise this. If difficult, PD, nightmare patients cannot recover or work in mental health, what are the mental health service doing with their service users? What are they working towards? There is such a blatant, screaming irony in the system, yet most are blind to it. I see people who have started out with good intentions, but they quickly get swallowed by the toxicity around them. At least two thirds of the employees talk about how they won’t come out of the NHS because of the bloody pension. Right now, I feel trapped by the money, and hate myself for it. I do not want to be that person. I have been that person, in the past, screaming at professionals that they are simply ‘doing it for the money’. That’s me, right now, in this moment in time, doing my job for the money. I care about the people I work with, but that care is overshadowed by the misery of what I am witnessing. I am at the bottom of the pile, sneered at for being a band 3 HCSW (I am asked ‘why don’t you go and do your nursing?’ at least twice a week). The hierarchy is real, and damaging, and people are made to feel shame.

I am in a quandary, a place of unease. I need to live, survive, so I need my wage. For a few years, I believed that people were not doing ‘this’ for the money, but we are. When our motivator is money, what have we become? Our priority is us, not the people accessing the service. It’s not a bad thing to want a wage, to have the right to earn a living. It’s certainly not a good thing, however, when the wellbeing of others is dependent on the wage being offered. Every day in work, I hear judgement and disdain, frustration and contempt for both users of the service and for the system as a whole, yet people continue to work in the same environment for many years. I am not the only one who hates their situation, but I see few, if any, doing something about it. Those in-office attitudes should remind us of how the system is run, and who is running it – a group of unhappy individuals, entrusted with the care and treatment of unwell individuals.

Mental health services need a complete reform, yet I do not see that happening any time soon. The good ones leave, the weak ones follow the crowd, and the leaders bully and intimidate. Stigma remains rife and continues to grow, and treatment is based on the egotistical needs of the practitioner. Where therapists have told me, ‘it’s not your fault’, they have instilled a deep shame within me regarding my reactions. My words are out there, on paper, as the model patient, and I cannot undo that. I was so desperately trying to please, that childlike need in me still searching for a mother, and professionals have either been blind or willing to take advantage of it. I’m trapped, and I am afraid of becoming ‘one of them’.

About the Author: I would like to be able to be transparent with who I am, but it is difficult to do so right now; Because of the institutional nature of current services – once in, you cannot have a voice, or as a service user, you don’t have a voice unless it is tokenistic. I hope to be able to come out of the NHS safely and be more open about my experiences.
– L

Mad At Work

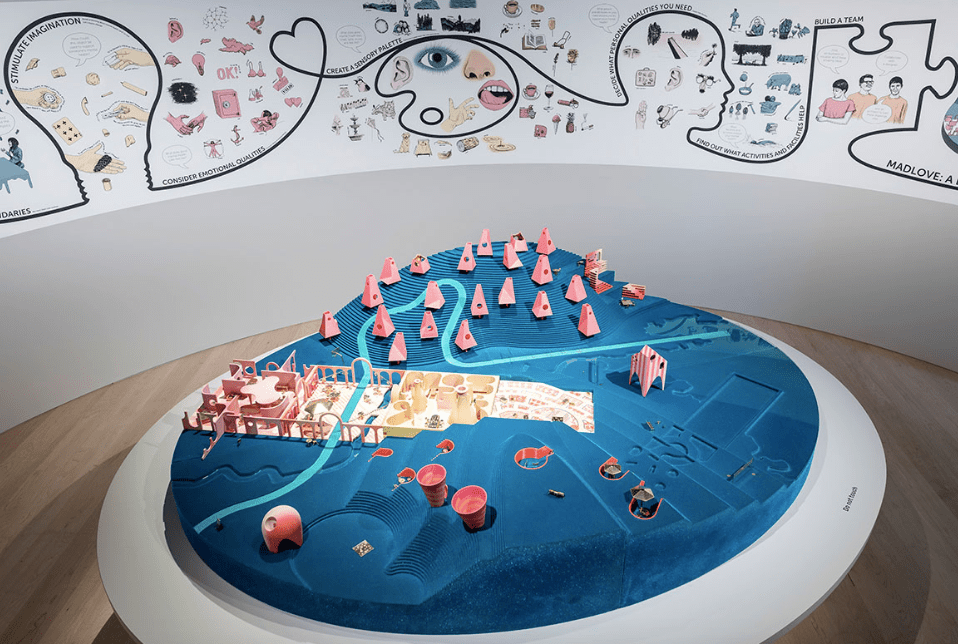
Madlove Designer Asylum project madlove.org.uk

Workplaces blame or punish individuals for madness, exclude mad people from work, and fail to recognise the role of work in making people mad in the first place. This is true even of measures supposedly designed to enable accessibility or promote mental health. Sick of this, I asked some members of radical and peer-led mental health groups, along with some friends and fellow weirdos, what they think would make it better to be ‘mad at work’. I collected all the responses, merging duplicates and re-writing stories into demands, to make the list below. 

Of course one of the best things workplaces could do for mad people would be to improve their economic conditions. Many folk brought up precarious employment as especially harmful, including short-term and zero-hour contracts, as well as people having to re-apply for or apply for funding for their own job. As long as there is capitalism there will be suffering for mad people at work, exclusion of mad people from work, and madness as a result of work. Although this list is not primarily about economic conditions, is not intended to justify wage labour or erase the harm it causes. 

Yet many of the suggestions made below are perfectly compatible with the logics of capitalism. Some mad people just want to get through the day however they can. They want to have a nap sometimes, dress more comfortably, mask less, not get lied to and – perhaps most of all – be subject to less surveillance. These things are cheap, straightforward, and would even enable mad people to ‘more productive’ workers within the grim logics of capitalism. So why are most items on our list still completely unimaginable?  

OUR DEMANDS

  1. No glass walls or doors for maximum privacy and minimum surveillance 
  2. All toilets to be accessible and all-gender
  3. Provision of private nap cubicles
  4. Abolition of gaps around toilet doors to allow for privacy for purging and panic attacks
  5. Provision of luxury harm reduction rooms, including beautiful soft furnishings, safety equipment (wipes, clean needles and razors, sharps bins), and gold boxes for everyone to keep their individual stuff in
  6. No dress codes or norm of dressing gowns, blankets, pyjamas, slippers, bare feet 
  7. No more defining mental health as the ability to work
  8. Abolition of counselling as gatekeeping for jobs
  9. End of the use of health and safety and risk assessments to punish and restrict autonomy of disabled people
  10. Abolition of small talk (replace with standard red/yellow/green communication badges every door) 
  11. Police uniforms for Human Resources & Occupational Health staff to make their roles clear
  12. Paid time in all workload models for collective organising (including but not limited to trade unionism, direct action, feminist consciousness raising and zine-making)
  13. Free workers’ canteens (with no coercive ‘health’ or ‘normal’ eating) 
  14. All contracts mandatorily available as job share 
  15. All workplaces to circulate and commit to Recovery in the Bin principles
  16. Worker feedback forms to be located over the shredder for clarity around purpose
  17. No more macho pretend-its-fine culture
  18. Actually flexible working hours
  19. Recognition of workers as humans for whom work is only one part of life 
  20. Abolition of workplace communication by whatsapp, ‘fun’ group chats that include bosses and all social media (except personal or political social media use at work)
  21. Time in all workload models for private, skilled, on-demand clinical supervision for anyone who works with ‘vulnerable’ groups
  22. Recognition that learning, not-knowing and lack of enjoyment are inevitable elements of work and not signs of unprofessionalism
  23. Resources to support working from home (e.g. printer and scanner)
  24. Option to get paid based on hours or on task, your choice, with no reduction in pay (maximum 25 hour work week either way)
  25. A sensory room with sensory toys AND integration of those things into rest of work place
  26. No forced disclosure ever
  27. Sound proofed screaming cubicles
  28. Screaming normalised everywhere, ear defenders supplied at all entrances
  29. Employers to pay employees’ union membership 
  30. No more suffering as a rite of passage
  31. Education for all employees about madness BY mad people
  32. Abolition of the idea of ‘professionalism’ (otherwise known as ableism, racism, misogyny, etc) 
  33. Abolition of ‘reasonable adjustments’, replacement with actually accessible workplaces including accessibility budget for all workers with no monitoring
  34. Wages for housework, care labour and all social reproduction 
  35. No more rest or breastfeeding areas in stationary cupboards 
  36. Repurposing of ‘common room’s for crafting, animal therapy, prayer, dart boards and punch bags with bosses faces on, meditation, etc. 
  37. No more token wellness activities or ‘pledges’
  38. More sharing of unsantized stories (NOT ‘it all got a bit tricky but I’m totally better and promotable now’)
  39. Abolition of requirement to perform trauma and healing for job 
  40. No more blaming our mental health for impossible working conditions

By Darcy Leigh.

The making of this list was inspired by the Mad Love Designer Asylum project, in which mad people design their own asylum.

This work is licensed under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.